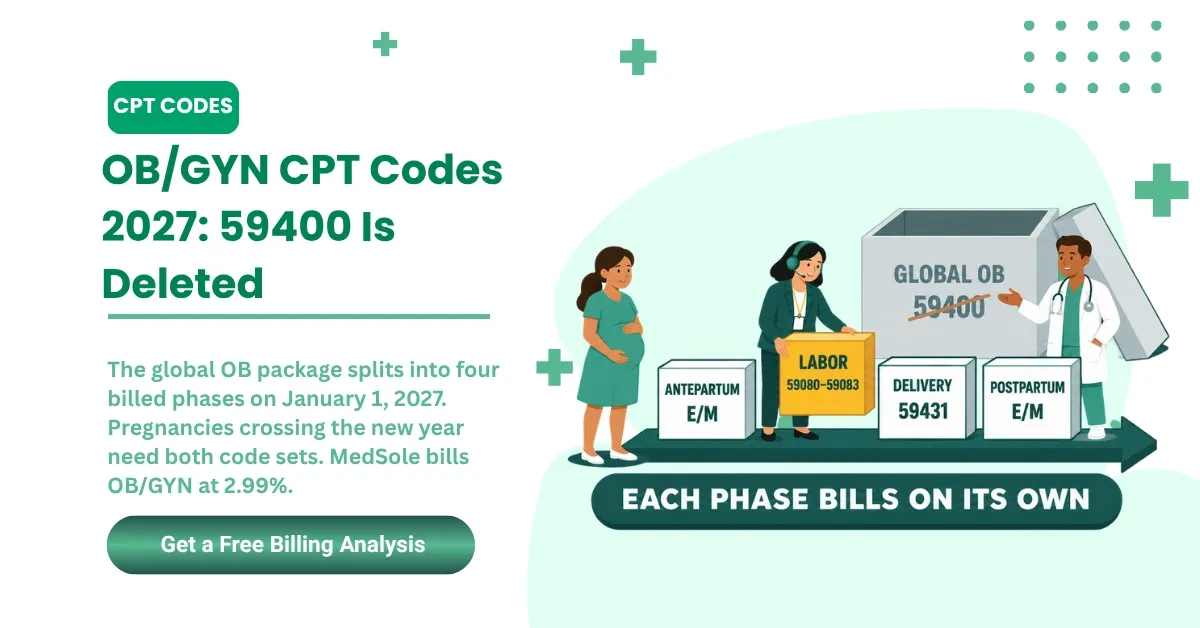




OB/GYN CPT codes change on January 1, 2027, when CPT replaces the global maternity package with four phases. CPT adds 12 maternity codes, including 59080 to 59083 for labor management and 59431 to 59434 for vaginal delivery and laceration repair. CPT announced no changes to gynecology procedure codes. Our 2027 CPT code changes guide covers the other specialties.
Starting January 1, 2027, CPT codes for maternity care split into two tracks. One code set covers care through the end of this year. A different, more granular set takes over for dates of service from January 1, 2027, and the two don't overlap the way a normal annual code update does.
Some payers moved first. From September 1, 2026, Aetna and MaineCare ask for E/M codes with modifier TH on prenatal visits. NC Medicaid encourages the same approach for patients due in 2027. The AMA starts full E/M reporting of antepartum care on January 1, 2027, so check each payer's policy.
This guide covers the OB/GYN CPT codes you're billing today, the exact codes replacing them in 2027, and the specific places claims are getting denied right now.
OB/GYN CPT Codes 2027 at a Glance
Pull the code you need from the table below. The 2026 column shows what you bill through December 31, 2026, and the 2027 column shows what changes on January 1.
|
Code |
What It Covers |
2026 |
2027 |
|
59400 |
Global OB package: antepartum, vaginal delivery, postpartum |
Active |
Deleted |
|
59510 |
Global OB package with cesarean delivery |
Active |
Deleted |
|
59080, 59081 |
Initial day labor management, straightforward or complex |
n/a |
New |
|
59082, 59083 |
Subsequent day labor management, straightforward or complex |
n/a |
New |
|
59431 |
Vaginal delivery, with or without episiotomy |
n/a |
New |
|
59432 |
Vaginal delivery after previous cesarean |
n/a |
New |
|
59433, 59434 |
Repair of third- or fourth-degree laceration |
n/a |
New |
|
59502 |
Cesarean delivery, primary |
n/a |
New |
|
59503 |
Cesarean delivery, repeat |
n/a |
New |
|
59504 |
Hysterectomy after cesarean delivery |
n/a |
New |
|
59623 |
Uterine tamponade |
n/a |
New |
|
99202 to 99215 |
Office E/M visits |
Active |
Also reports prenatal and postpartum visits |
|
76801 |
Complete first-trimester obstetric ultrasound |
Active |
No change announced |
|
99396 |
Preventive visit, established patient, ages 40 to 64 |
Active |
No change announced |
|
99459 |
Add-on for pelvic exam practice expense |
Active since 2024 |
No change announced |
|
88175 |
Automated cervical cytology, Pap smear |
Active |
No change announced |
|
57454 |
Colposcopy with cervical biopsy and endocervical curettage |
Active |
No change announced |
|
58120 |
Dilation and curettage, non-obstetric |
Active |
No change announced |
|
59820 |
Treatment of missed abortion, first trimester |
Active |
No change announced |
|
Modifier TH |
Obstetrical treatment or services, prenatal or postpartum |
Some payers from September 1 |
Payer policy varies |
|
Want this code list on paper? Get the printable 2027 OB/GYN CPT codes PDF with a free billing analysis of your OB/GYN claims. We reply within one business day. |
What Changed in OB/GYN CPT Codes for 2027
Why the Global Maternity Code Is Going Away
A single code has represented nine months of pregnancy care for more than three decades. That code worked when one doctor saw a patient from her first prenatal visit through her six-week checkup. It stopped working once patients started seeing multiple providers across a single pregnancy.
The American Medical Association's CPT Editorial Panel approved a full restructuring of maternity care codes at its September 2025 meeting, after work with ACOG and other specialty societies. The panel replaced the global package with four phases, each billed on its own: antepartum, labor management, delivery, and postpartum.
Three real-world patterns drove the change. Patients now see multiple, sometimes unaffiliated providers across a single pregnancy. Rural patients get transferred to higher-acuity centers mid-pregnancy more often than the old code assumed. More antepartum care now follows a tailored visit schedule with telehealth built in, replacing the fixed visit pattern the global code was built around. For a full walkthrough of the change from the source, see AMA's coding primer webinar on the restructure.
The Exact Codes Changing in 2027
Thirty-five OB/GYN CPT codes change in total. The AMA deletes 17, adds 12, and revises six. Add a labor management code, 59080 to 59083, to each delivery when labor management happens.
|
Deleted Code (2026) |
Report in 2027 |
|
59400 |
E/M for each antepartum visit; 59080 to 59083 when labor management is performed; 59431; E/M for each postpartum visit |
|
59409, 59410 |
59431, plus 59080 to 59083 when performed; postpartum visits as E/M |
|
59425, 59426 |
E/M code for each antepartum encounter |
|
59430 |
E/M code for each postpartum encounter |
|
59510 |
E/M antepartum and postpartum visits; 59502 or 59503; a labor management code when labor came first |
|
59514, 59515 |
59502 for a primary cesarean, 59503 for a repeat cesarean; postpartum visits as E/M |
|
59525 |
59504 |
|
59610, 59612, 59614 |
59432, plus labor management when performed; antepartum and postpartum visits as E/M |
|
59618, 59620, 59622 |
59503 for a repeat cesarean after a failed trial of labor, plus labor management when performed |
|
59050 |
59051, revised to cover fetal monitoring during labor by a consulting physician |
The new codes fall into four families. 59080 and 59081 cover initial day labor management, split by straightforward or complex. 59082 and 59083 cover subsequent days using the same split. 59433 and 59434 report third- and fourth-degree laceration repair, now billed apart from the delivery code itself. 59504 covers a hysterectomy performed during the same session as a cesarean delivery. 59623 is a new procedure code for uterine tamponade, used to manage postpartum hemorrhage with a balloon, catheter, or packing device. It does not cover pharmacologic management of hemorrhage. This entire mapping comes from AMA's published 2027 maternity coding guidelines.
CPT also revises six existing maternity codes for 2027. Recheck each descriptor in the CPT 2027 codebook before you update your chargemaster, since the revised wording sets what each code covers from January 1.
Revised Maternity CPT Codes for 2027
|
Code |
Service |
|
59051 |
Fetal monitoring during labor by consulting physician |
|
59300 |
Repair of first- or second-degree episiotomy or laceration, by other than attending physician |
|
59412 |
External cephalic version |
|
59414 |
Delivery of placenta only (separate procedure) |
|
59898 |
Unlisted laparoscopy procedure, maternity care |
|
59899 |
Unlisted procedure, maternity care |
Labor Management CPT Codes 59080 to 59083
Labor management codes report the work of managing labor, once per calendar date. Use 59080 or 59081 on the initial day, when a provider first takes over care in that facility stay. Use 59082 or 59083 on each later day, including a delivery date when labor management happens.
Complexity sets the level, not time. Labor counts as straightforward only when it meets every AMA criterion, such as a single fetus in vertex position and no prior cesarean. Any other labor is complex. Duration matters only when the physician diagnoses prolonged labor.
Don't report 99221 to 99236 by the same physician or group on any date you report 59080 to 59083. When the patient came from the ED or the office on an initial labor day, that earlier E/M can be reported with modifier 25.
Labor Management Codes by Day and Level
|
Code |
Day |
Level |
|
59080 |
Initial day |
Straightforward |
|
59081 |
Initial day |
Complex |
|
59082 |
Subsequent day |
Straightforward |
|
59083 |
Subsequent day |
Complex |
Vaginal Delivery and Laceration Codes 59431 to 59434
Report 59431 for a vaginal delivery, with or without episiotomy, and 59432 for a vaginal birth after a previous cesarean. Both include first- and second-degree laceration repair. Add 59433 for a third-degree repair or 59434 for a fourth-degree repair done at the time of delivery.
A provider who didn't perform the delivery reports a later repair with 59300. Don't report 59300 with 59431 or 59432 when the same specialty and group bill the delivery. Same-day postpartum care after the birth sits inside the delivery code.
Cesarean Delivery Codes 59502 to 59504
Report 59502 for a primary cesarean and 59503 for a repeat cesarean. A failed trial of labor after a prior cesarean ends in a repeat cesarean, so it takes 59503. When a planned vaginal delivery converts to cesarean, report only the cesarean code.
Use 59504 for a subtotal or total hysterectomy in the same session as the cesarean, by the same or a different physician. When one physician does both, add modifier 51 to 59504. Report a tubal ligation during the hysterectomy with 58611.
Uterine Tamponade CPT 59623
CPT 59623 reports uterine tamponade for postpartum hemorrhage with a balloon, catheter, vacuum device, or packing material. Don't report it for medication-only management of the bleeding. Document the device and the reason for placement in the delivery note, since payers see this code for the first time in 2027.
Antepartum and Postpartum Care in 2027: E/M by Setting
From January 1, 2027, you report each antepartum visit with the E/M code for its setting. Use 99202 to 99215 in the office, 98000 to 98015 for telemedicine, 98016 for a virtual check-in, and 99341 to 99350 at home. Ultrasounds and fetal MRI bill on their own lines.
Postpartum care works the same way. Each postpartum encounter gets its own E/M code, while same-day care after the birth stays inside the delivery code. For a later inpatient day, use 99231 to 99233, and don't bill 99238 or 99239 when discharge falls on the delivery date.
Pregnancies That Span 2026 and 2027
The AMA counts antepartum visits by calendar year. For 2026, bill 1 to 3 visits as E/M codes, 4 to 6 as 59425, and 7 or more as 59426. Submit once the last 2026 visit is done. Every antepartum visit on or after January 1, 2027, is an E/M.
A December 2026 delivery still takes the 2026 global code, such as 59400. The AMA says a postpartum visit on or after January 1, 2027, could be reported as an E/M. The global code already covers routine postpartum care, though. Confirm each payer's rule before you bill it.
Payers also differ on modifier TH, the HCPCS modifier for prenatal or postpartum services. The table below shows what four payers published for visits on or after September 1, 2026. Confirm your own contracts, since many plans haven't published guidance yet.
Modifier TH Guidance From Four Payers
|
Payer |
Guidance for Prenatal Visits From September 1, 2026 |
|
Aetna |
Bill preventive prenatal visits for patients expected to deliver in 2027 with the E/M code and modifier TH |
|
MaineCare |
Append TH to all maternity care E/M codes, effective September 1, 2026 |
|
NC Medicaid |
Encourages E/M 99202 to 99215 with TH when delivery or postpartum care is expected after January 1, 2027 |
|
MassHealth |
May bill E/M with TH when the first prenatal visit falls on or after September 1, 2026 |
|
Patients due in 2027 already on your schedule? We check each prenatal claim against the payer's TH and E/M rules. Get a free billing analysis of your OB claims. We reply within one business day. |
CMS 2027 Proposed Rule and Maternity Payment
CMS proposed values for the new maternity codes in its 2027 Physician Fee Schedule proposed rule, released July 14, 2026, per the AMA summary. It also asked for comments on 15 G-codes that would keep the old global package for Medicare. ACOG and the AMA oppose that option.
CMS also asked whether to drop four E/M visits from its utilization estimate and move that value into labor and delivery, per the AAFP summary. It accepts the RUC's 15.56 work RVUs for 59504. The proposed conversion factor drops to $32.8409 from $33.4009.
The final rule, expected in early November, decides which structure Medicare uses. If CMS adopts the G-codes, you could bill Medicare one way and commercial plans another. Track each payer's choice before January claims go out.
Gynecology Codes Don't Change
Hysterectomy, colposcopy, IUD management, and every other gynecology code in this OB/GYN CPT codes guide carries into 2027 with no change announced. The 2027 restructuring touches maternity care only.
2027 Maternity Coding Scenarios, Worked Through
These five cases cover the questions coders ask most about the new codes. Each answer follows the AMA's 2027 maternity guidelines. Check payer policy where a payer publishes its own rule, such as for modifier TH.
VBAC With Complex Labor Management on January 1, 2027
A patient is admitted on January 1, 2027, for a trial of labor after a prior cesarean. She receives complex labor management and has a vaginal birth that day. Report 59081 for initial day complex labor management and 59432 for the vaginal birth after cesarean.
A prior cesarean rules out straightforward labor, so the level is complex. Don't add 99221 to 99223 for the admission by the same group. Don't bill same-day postpartum care either, since 59432 includes it.
What Labor Management Codes 59080 to 59083 Are Based On
The level depends on the complexity of labor management that calendar day, not on time, unless the physician diagnoses prolonged labor. The day type depends on whether this provider is starting care in the facility stay. Report one code per date at the highest level provided.
Fewer Than Four Prenatal Visits in 2026
A 2026 patient with one to three antepartum visits gets an E/M code for each visit. Four to six visits take 59425, and seven or more take 59426, billed after the last 2026 visit. From January 1, 2027, every antepartum visit is an E/M, whatever the count.
December 2026 Delivery With a January 2027 Postpartum Visit
Bill the 2026 global code, such as 59400, for a delivery on or before December 31, 2026. The AMA notes that a postpartum visit in 2027 could be reported with an E/M code. The global code already covers routine postpartum care, so confirm the payer's rule first.
Scheduled vs Unscheduled Cesarean in 2027
A scheduled cesarean with no labor takes 59502 or 59503 alone, with no labor management code. When a patient labors first and then needs an unplanned cesarean, add complex labor management, 59081 or 59083, for that date. A failed trial of labor after cesarean goes to 59503.
|
Your labor notes will set the 2027 code level. Document each straightforward criterion, or the reason labor was complex, in every day's note. Get a free billing analysis of your L&D documentation. We reply within one business day. |
2026 Global OB Package Codes (Through December 31, 2026)
Among all the OB/GYN CPT codes in active use, four global codes carry practices through December 31, 2026: 59400, 59510, 59610, and 59618. CPT deletes all four on January 1, 2027. Each one bundles three phases of pregnancy care into a single payment, and each one comes with a strict included and excluded list.
What's Included in the Global Package
The global package covers routine antepartum visits, uncomplicated labor management, the delivery itself, first- or second-degree laceration repair, and routine postpartum care within the standard window. A single provider or group bills all of it under one code, one time.
What's Excluded from the Global Package
Ultrasounds, amniocentesis, non-stress tests, and external cephalic version all bill outside the global code. So does care for a condition unrelated to the pregnancy, like a sinus infection treated during a prenatal visit. Any antepartum visit count that falls outside the routine pattern moves to itemized billing instead, which the next section covers.
The global code depends on one condition holding true: a single provider or group, under one tax ID, delivering all three phases of care to one payer. Break any part of that condition and itemized billing takes over.
When the Global Code Doesn't Apply: Itemized OB Codes
A patient transfers practices mid-pregnancy. A different provider handles the delivery. Care ends before the six-week postpartum visit happens. Any of these situations moves a claim out of the global package and into a different corner of OB/GYN CPT codes: the itemized set.
|
Situation |
Code to Bill in 2026 |
2027 |
|
Your practice gave 4 to 6 antepartum visits, then the patient transferred out |
59425 |
Deleted; E/M per visit |
|
Your practice gave 7 or more antepartum visits, then the patient transferred out |
59426 |
Deleted; E/M per visit |
|
You delivered the baby, but another provider handles postpartum care |
59409 |
Deleted; 59431 |
|
You delivered the baby and will also handle the postpartum visit |
59410 |
Deleted; 59431 plus postpartum E/M |
|
You handled only the postpartum visit, with no prior antepartum or delivery care |
59430 |
Deleted; postpartum E/M |
|
Your practice saw the patient for only 1 to 3 antepartum visits |
Standard E/M codes, not 59425 or 59426 |
E/M per visit |
That last row catches more practices than it should. A patient seen once, twice, or three times before transferring gets billed with standard E/M codes for each visit. Code 59425 requires a minimum of four visits, and billing it for three creates a denial that won't survive an appeal.
A root-cause denial review catches a visit-count mismatch like this while the claim is still in queue, before it turns into a denial. See how MedSole's denial review process works.
Obstetric Ultrasound CPT Codes: Which One, and Can You Bill Two Together
Ultrasound codes are the OB/GYN CPT codes billing teams look up most often, and the wrong one gets picked more than any other category in this guide.
76801 vs 76805: Which Trimester, Which Code
CPT 76801 covers a complete transabdominal ultrasound before 14 weeks 0 days of pregnancy. CPT 76805 takes over at 14 weeks 0 days and continues through the rest of the pregnancy. Gestational age at the time of the scan decides the code, independent of when the visit was scheduled.
76811 vs 76805: Standard Scan or Detailed Anatomy Survey
CPT 76811 is a higher tier of 76805, a detailed anatomy survey ordered only when a specific medical indication exists, such as a suspected fetal anomaly. Maternal-fetal medicine typically performs or supervises this scan, reserved for cases with that specific indication rather than routine second-trimester screening.
76815, 76816, and 76817: Limited, Follow-Up, and Transvaginal
CPT 76815 is the limited scan, usable in any trimester when a single narrow question needs an answer, such as confirming a heartbeat or checking placental location. It also serves as the correct fallback when a first-trimester scan was meant to be complete under 76801 but a required element couldn't be visualized and documented. CPT 76816 covers a follow-up or repeat scan later in the same pregnancy. CPT 76817 is the transvaginal approach, used when the transabdominal view alone doesn't answer the clinical question.
Can These Codes Be Billed Together
Many of these pairs can be billed on the same date, but only with separate, documented medical necessity for each one. A transabdominal scan followed by a transvaginal scan because the first view was insufficient supports billing both. A transabdominal scan followed by a transvaginal scan with no documented reason for the second one invites a bundling denial or a multiple-procedure reduction. The professional and technical component split matters here too, especially when one physician reads the images and a different facility performs the scan. Read the full technical component breakdown.
Pregnancy Loss and Miscarriage CPT Codes
CPT 59812 and CPT 59820 get confused, and the confusion costs real money on appeal. 59812 treats an incomplete abortion: the miscarriage has already started, and some tissue has passed, in any trimester. 59820 treats a missed abortion: the pregnancy has stopped developing, but nothing has passed yet, and this code applies only in the first trimester. CPT 59821 is the second trimester version of the same clinical picture, a distinction several billing guides skip.
CPT 59840 and CPT 59841 split by method rather than clinical status. 59840 reports an induced abortion by dilation and curettage. 59841 reports dilation and evacuation, typically used further into a pregnancy once suction alone can't complete the procedure. Every code number in this section is checked against the current CPT guideline language for these procedures.
One question decides the correct code across this category: has tissue already passed, and which trimester applies. The clinical status documented at the time of the procedure is what points a coder to the right one, well before the general term "miscarriage" enters the chart note.
None of these pregnancy loss codes change for 2027. The maternity restructure leaves 59812, 59820, 59821, 59840, and 59841 in place. Your 2026 coding rules for miscarriage and D&C carry into January, including the trimester split.
Well-Woman and Preventive Exam CPT Codes
Well-woman and Pap smear codes come up constantly, and they're also where a single reversed modifier causes the most damage.
Preventive Visit Codes by Age, 99384 to 99397
New patients get preventive visit codes 99384 through 99387, split into four age bands. Established patients get 99394 through 99397, using the same four bands: 12 to 17, 18 to 39, 40 to 64, and 65 and older. A patient counts as established if any physician in the same specialty and same group has seen her for a face-to-face visit within the past three years. Miss that window by even a day, and the visit reverts to a new-patient code.
Modifier 25 causes more denials in this category than any other error. When a patient comes in for a scheduled well-woman exam and the physician also addresses a separate, significant problem in the same visit, the problem-oriented E/M code carries modifier 25. The preventive code does not. Billing teams reverse this pairing often, and the reversal bundles the whole claim.
Pap Smear and Cervical Cytology Codes
CPT codes 88141 through 88175 cover cervical and vaginal cytology, and the specific code depends on the collection method and the screening tier used. For Medicare patients, the pathway looks different. Original Medicare doesn't pay for the standard 99384 through 99397 preventive codes at all, so two Medicare-specific codes fill that gap.
Medicare Specific Codes: Q0091 and G0101
Q0091 covers obtaining, preparing, and conveying a screening Pap smear to the lab. G0101 covers the pelvic and clinical breast exam. Medicare pays for both on a two-year cycle for average-risk patients, and annually for high-risk patients or those with an abnormal Pap result in the past three years. Bill G0101 alongside a same-day E/M service with modifier 25 attached, and don't report it on the same date as the routine 99384 through 99397 codes, since those already include the age-appropriate exam. CMS spells out the frequency rules in its own Medicare wellness visit coverage rules.
Add-on code 99459 sits next to this cluster and gets misapplied often. Introduced in 2024, it captures the practice expense of a pelvic exam performed alongside an eligible office visit, consult, or preventive code: staff time, a speculum, and supply costs, distinct from the physician's own work. A chaperone's presence is typical documentation for this code, though the code's own language doesn't require one. A primary code from a specific list is required instead, and G0101 or Q0091 don't qualify, since those two HCPCS codes already build practice expense into their own valuation.
Confirming which of these OB/GYN CPT codes fits a patient's age and payer, before the claim goes out rather than after a denial arrives, is the kind of check a coding review is built to run. Read the full 99396 age and modifier rules or the 18 to 39 preventive bracket.
|
Well-woman visits with a problem visit attached? We check modifier 25 placement and the 99459 add-on before each claim goes out. Get a free billing analysis of your GYN claims. We reply within one business day. |
Common Gynecologic Procedure CPT Codes
This next set of OB/GYN CPT codes covers table stakes territory, the procedures every GYN practice bills weekly. Colposcopy splits into four codes based on what accompanies the exam. CPT 57452 covers the exam alone, with no tissue taken. CPT 57454 adds both a cervical biopsy and endocervical curettage. CPT 57455 adds a cervical biopsy only, with no curettage. CPT 57456 adds curettage only, with no biopsy. Mixing these up is one of the fastest ways to undercode or overcode a routine colposcopy visit.
CPT 58100 covers an endometrial biopsy. CPT 58120 covers dilation and curettage for a non-obstetric indication, a code worth keeping separate in your own mind from the pregnancy-loss codes covered earlier in this guide, since payers treat them as different clinical events. CPT 58558 covers hysteroscopy with biopsy or polypectomy. CPT 58300 and 58301 cover IUD insertion and removal.
Hysterectomy coding depends on surgical approach. CPT 58150 covers a total abdominal hysterectomy. The 58260 range covers a vaginal approach. The 58570 range covers a laparoscopic approach, and uterine weight above or below 250 grams changes which specific code in that range applies. The AMA maintains the full code set behind every number in this section at its own CPT code resources.
The single most common denial in this category comes from billing a colposcopy and an E/M visit on the same date without documenting a distinct, separately identifiable reason for that E/M. Payers bundle the two automatically when that documentation is missing.
The table below groups the common GYN procedure codes by service. None of them change in the 2027 maternity restructure. Use it to check charge entries before your year-end chargemaster review, alongside the CPT 2027 codebook.
Common GYN Procedure CPT Codes (2026 and 2027)
|
Code |
Procedure |
2027 Status |
|
57452 |
Colposcopy, exam only |
No change announced |
|
57454 |
Colposcopy with cervical biopsy and endocervical curettage |
No change announced |
|
57455 |
Colposcopy with cervical biopsy |
No change announced |
|
57456 |
Colposcopy with endocervical curettage |
No change announced |
|
58100 |
Endometrial biopsy |
No change announced |
|
58120 |
Dilation and curettage, non-obstetric |
No change announced |
|
58558 |
Hysteroscopy with biopsy or polypectomy |
No change announced |
|
58300 |
IUD insertion |
No change announced |
|
58301 |
IUD removal |
No change announced |
|
58150 |
Total abdominal hysterectomy |
No change announced |
|
58260 to 58294 |
Vaginal hysterectomy family |
No change announced |
|
58570 to 58573 |
Laparoscopic total hysterectomy, split at 250 grams |
No change announced |
|
58611 |
Tubal ligation at cesarean or other intra-abdominal surgery, add-on |
No change announced |
OB/GYN Billing Modifiers That Matter
Modifiers don't get their own code number, but they change how every one of the OB/GYN CPT codes above gets paid.
|
Modifier |
Trigger Condition |
OB/GYN Example |
|
25 |
Separate, significant E/M on the same day as a procedure or preventive visit |
A problem visit with a well-woman exam, or an office visit before admission on an initial labor management day |
|
59 and the X modifiers |
Two services an NCCI edit bundles, performed as separate and distinct |
Procedures at separate sites, such as the cervix and the endometrium, when an NCCI edit pairs them |
|
51 |
Multiple procedures in one session |
59504 when the same physician performs the cesarean and the hysterectomy |
|
22 |
A delivery or procedure that takes far more work than usual |
A cesarean complicated by dense adhesions from prior surgery, with an operative report attached |
|
24 |
Unrelated E/M during a global period |
A sinus infection treated during a 2026 global postpartum window |
|
TH |
Obstetrical treatment or services, prenatal or postpartum |
Prenatal E/M visits for payers that ask for TH, such as Aetna and MaineCare |
Modifier 59 and its more specific X modifier alternatives, XE, XS, XP, and XU, flag two services that would normally bundle as separate and distinct. CMS lays out the underlying bundling logic in its own National Correct Coding Initiative Policy Manual. Payers prefer the specific X modifier over the general 59 whenever one applies. Read the full X modifier rules. Modifier 22 needs an operative report attached every time. The modifier alone, without that report, tells a payer nothing about why the case took more work than usual.
Modifier 24 covers care unrelated to a delivery or surgery during that procedure's global period, and it belongs on the E/M code, not the original procedure code. See the full global period rules. Getting this backward is a common, avoidable source of denied postpartum visits.
Where OB/GYN Claims Get Denied
Most denials on OB/GYN CPT codes trace back to four repeat scenarios, not forty different problems. A global OB code gets billed when the patient transferred practices mid-pregnancy, and the claim doesn't match the tax ID or visit history the payer already has on file. A same-day E/M and preventive visit go out without modifier 25, and the system bundles them without a manual review. A colposcopy and biopsy get billed together with no documentation showing the biopsy came from a distinct site or session. An antepartum E/M claim goes to a payer that asks for modifier TH, and the claim leaves it off.
January 2027 adds three new risks. A deleted global code such as 59400 on a 2027 delivery will fail payer edits. A complex labor management code without documented complexity invites review. An inpatient E/M from the same group on any labor management date draws a denial.
Each one traces back to a single missing piece of documentation. That distinction matters, because it changes the fix. A coding error needs a new code. A documentation gap needs a different chart note next time. See a bundling denial worked through in detail.
A root-cause denial review works through this kind of pattern: categorizing the denial, fixing the claim in front of you, and correcting the workflow that produced it so the same denial stops recurring on next month's report. See how root-cause denial review works.
|
Same OB denials every month? Our denial management team traces each one to its root cause and fixes the workflow behind it. Start with a free billing analysis. We reply within one business day. |
What to Look for in an OB/GYN Billing and Credentialing Partner
Everything above in this guide is something your own billing team can learn and apply. Whether they have the time to apply it across every claim, every payer, and every code update is a separate question.
Four things separate a specialty billing partner from a general one:
- Published, transparent pricing, instead of a quote you request and wait for
- Coders who already know the 2027 maternity codes and payer TH rules, not general medical billing knowledge applied to OB/GYN by default
- Fast credentialing, since a delayed enrollment blocks every claim behind it no matter how clean the coding is
- One team handling both billing and credentialing, instead of two vendors that don't talk to each other
MedSole RCM builds around those four points. Medical billing starts at 2.99% of collections. There's no setup fee and no long-term contract. Credentialing runs $99 per insurance enrollment, handled by the same team and under the same rate structure as the billing itself.
|
Service |
MedSole RCM Terms |
|
Medical billing |
2.99% of collections, no setup fee, no long-term contract |
|
Credentialing |
$99 per insurance |
When the coding questions in this guide point to a bigger workflow gap than one denied claim, start with a free billing analysis. We review your OB/GYN claims, flag what's costing you, and reply within one business day.
|
Your OB/GYN billing at 2.99% of collections. No setup fee and no long-term contract. Credentialing runs $99 per insurance. Get a free billing analysis and we reply within one business day. |
OB/GYN CPT Codes: Frequently Asked Questions
What are the OB/GYN CPT codes for 2026?
Gynecology procedures use the female genital system codes 56405 to 58999, and maternity care uses 59000 to 59899. Office visits use the E/M codes, and 99459 adds pelvic exam practice expense. The 2026 global maternity codes, such as 59400 and 59510, stay valid through December 31, 2026. The GYN procedure codes carry into 2027 with no change announced, so your colposcopy, biopsy, and hysterectomy coding stays the same.
What are the changes in OB-GYN coding for 2027?
Thirty-five maternity codes change on January 1, 2027. CPT deletes 17, including the global codes 59400 and 59510, adds 12, and revises six. Care splits into antepartum, labor management, delivery, and postpartum, with E/M codes for the visits. CPT announced no GYN procedure code changes. In its proposed rule, CMS also asked about G-codes that would keep a global package for Medicare.
How do you code a VBAC with complex labor management on the same day in 2027?
Report 59081 and 59432. The patient's first day of labor care in that stay makes it an initial day, and a prior cesarean makes the labor complex. Don't add an inpatient admission E/M from the same group on that date. Same-day postpartum care is part of 59432, so it doesn't get its own line. Document the complexity in that day's labor note.
What are labor management codes 59080 to 59083 based on?
They're based on the complexity of labor management provided on that calendar day. Straightforward requires every AMA criterion, and anything else is complex. The day type, initial or subsequent, depends on when the provider takes over care in the facility stay. Time sets the level only when the physician diagnoses prolonged labor. Report one labor management code per date at the highest level.
How do you bill fewer than four prenatal visits in 2026?
Bill each visit with an E/M code. The AMA's 2026 rules send one to three antepartum visits to E/M, four to six visits to 59425, and seven or more to 59426. Submit the antepartum claim once you know the 2026 visit count. From January 1, 2027, every antepartum visit is an E/M, whatever the count or the payer's old rules.
How do you bill a December 2026 delivery with a January 2027 postpartum visit?
Bill the 2026 global code, such as 59400 or 59510, for the delivery. The global code already includes routine postpartum care. The AMA says a postpartum service on or after January 1, 2027, could be reported with an E/M code. Confirm the payer's rule before you send that claim. Document the visit date and the delivery date.
What does CPT code 59400 include?
CPT 59400 includes routine antepartum visits, uncomplicated labor, the vaginal delivery, and first- or second-degree laceration repair. It also covers routine postpartum care, under one payment to one provider or group. Ultrasounds, amniocentesis, non-stress tests, and external cephalic version bill apart. CPT deletes 59400 on January 1, 2027, and E/M visits plus 59080 to 59083 and 59431 replace it.
What does CPT code 59409 include?
CPT 59409 covers a vaginal delivery only, billed when the delivering provider doesn't bill the postpartum care. A provider who delivers and handles postpartum care bills 59410 instead. Both codes run through December 31, 2026. From January 1, 2027, report 59431 for the delivery, a labor management code when performed, and E/M for postpartum visits.
What replaced CPT 59400 in 2027?
No single code replaces 59400. From January 1, 2027, you bill each antepartum visit as an E/M and labor management as 59080 to 59083 when performed. The vaginal delivery takes 59431, and each postpartum visit takes an E/M. A VBAC uses 59432, and third- or fourth-degree repairs add 59433 or 59434. Ultrasounds still bill on their own lines.
What is the CPT code for a cesarean delivery in 2027?
Report 59502 for a primary cesarean and 59503 for a repeat cesarean, starting January 1, 2027. Add 59504 when a hysterectomy follows in the same session. In 2026, the global codes 59510 and 59618 and the cesarean codes 59514 and 59515 still apply. A scheduled cesarean without labor takes no labor management code, while labor before an unplanned cesarean adds 59081 or 59083.
Is modifier TH required for prenatal visits?
It depends on the payer. TH is the HCPCS modifier for obstetrical treatment or services, prenatal or postpartum. ACOG, AAFP, and others recommended that payers adopt it. Aetna and MaineCare ask for TH on prenatal E/M visits from September 1, 2026, NC Medicaid encourages it, and MassHealth allows it. Check each contract, since many plans haven't published a TH rule yet.
What is the difference between CPT 76801 and 76815?
CPT 76801 is a complete transabdominal ultrasound performed before 14 weeks 0 days of pregnancy. CPT 76815 is a limited scan usable in any trimester, built to answer one narrow clinical question rather than complete the full standard survey. A first-trimester scan that couldn't visualize every required element under 76801 gets billed as 76815 instead.
What is the CPT code for D&C?
The answer depends on the clinical picture. CPT 58120 covers a non-obstetric dilation and curettage, used for conditions like abnormal bleeding. CPT 59812 and CPT 59820 cover the same procedure performed for a pregnancy loss, split by whether tissue has already passed. Confusing these three codes is one of the most common billing errors in this specialty.
What is the difference between CPT codes 59812 and 59820?
CPT 59812 treats an incomplete abortion, where the miscarriage has already started and some tissue has passed, and it applies in any trimester. CPT 59820 treats a missed abortion, where the pregnancy has stopped developing but nothing has passed yet, and it's restricted to the first trimester alone.
Is CPT 59820 still valid in 2027?
Yes. CPT 59820, treatment of a missed abortion in the first trimester, stays in place for 2027. The maternity restructure deletes the global and delivery codes but leaves the pregnancy loss codes alone. 59812, 59821, 59840, and 59841 also carry into 2027 with no change announced. Code them by trimester and by whether tissue has passed, as in 2026.
What is the CPT code for a GYN office visit?
A GYN visit addressing a specific problem, such as pelvic pain or abnormal bleeding, uses the standard office visit codes: 99202 through 99205 for a new patient, 99212 through 99215 for an established one. An annual well-woman exam uses a different set of codes, the age-banded preventive codes covered earlier in this guide. Mixing the two up is a frequent source of denials on both sides.
What CPT code is used for a prenatal visit in 2027?
From January 1, 2027, each prenatal visit gets the E/M code for its setting. Use 99202 to 99215 in the office, 98000 to 98015 for telemedicine, and 99341 to 99350 at home. Some payers also ask for modifier TH. In 2026, the AMA's visit-count rules still apply: E/M for one to three visits, then 59425 or 59426.
What CPT code is used for a postpartum visit in 2027?
Report each postpartum visit with the E/M code for its setting, such as 99212 to 99215 in the office. Same-day care after the birth stays inside the delivery code. For a 2026 delivery billed with a global code, routine postpartum care is already included, so check the payer before you bill a 2027 E/M. For a 2027 delivery, every postpartum visit is its own E/M.
What are OB/GYN coding guidelines?
Two systems govern OB/GYN billing: CPT for procedures and visits, maintained by the American Medical Association, and ICD-10-CM for diagnoses, maintained by CMS and the CDC. ACOG works with the AMA's CPT Editorial Panel on maternity-specific updates, which is why ACOG's own guidance carries real weight on questions like the 2027 restructure and payer use of modifier TH.
What should an OB/GYN practice look for in a billing and credentialing partner?
Look for published pricing, coders who know the 2027 maternity codes, fast credentialing, and one team for billing and credentialing. MedSole RCM charges 2.99% of collections for billing, with no setup fee and no long-term contract. Credentialing costs $99 per insurance. Request a free billing analysis to see what your practice would pay, and we reply within one business day.
Is there an OB/GYN CPT codes cheat sheet PDF?
Yes. The 2027 glance table near the top of this guide lists the new maternity codes, the deleted global codes, and the common GYN codes. MedSole RCM also sends a printable 2027 OB/GYN CPT codes PDF with a free billing analysis of your claims. We reply within one business day. Use the table until the PDF arrives.
OB/GYN CPT Codes in 2027: The Bottom Line
2026 codes stay active through December 31 of this year. The 2027 restructure replaces the global maternity package, phase by phase. Some payers already ask for modifier TH on prenatal visits.
If your billing team is still confirming where the practice stands on any of this, start with a free billing analysis. We review your OB/GYN claims, show where 2027 changes hit your revenue, and reply within one business day.